
Opinion|Videos|October 7, 2026
Personalizing MDD Treatment: Evidence, Experience, and Patient Values
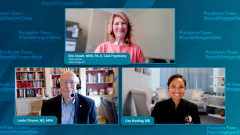
Precision medicine looks different in psychiatry than in oncology. The panel discusses why personalizing MDD care starts with a complete patient history, and how clinical experience, evidence, and patient goals combine to guide treatment.
Advertisement
This episode, "Personalizing MDD Treatment: Evidence, Experience, and Patient Values," turns to what personalizing treatment actually requires beyond picking a medication.
Dr. Harding argues that psychiatry lags behind more mature specialties when it comes to personalization. She points to oncology, where concrete staging and genetic testing identify a patient's cancer subtype and match it to a targeted treatment. Psychiatry has no equivalent biomarker, so personalization instead starts with gathering the patient's entire story rather than a lab result.
She explains that many symptoms go unreported because patients don't realize they're relevant. Few clinicians ask female patients about their sex drive, for example, and symptoms like brain fog, low libido, weight change, and thinning skin can overlap confusingly with perimenopause, ADHD, and depression at once. Trained in Cuba's socialized medicine system, she learned that roughly ninety percent of diagnosis comes from history and a physical exam rather than testing. In psychiatry, that physical exam is the mental status exam. Without a correct diagnosis first, she says, treatment becomes guesswork, and she notes that patients labeled with unipolar depression sometimes never had it, delaying the bipolar diagnosis that would actually explain their nonresponse.
Dr. Citrome shifts to how individualized care is taught today. He describes three components that must be weighed together: the clinician's own clinical experience, the patient's values and preferences, and the current scientific evidence. He notes that shared decision making and motivational interviewing, tools he never encountered during his own training, have since become central to personalized care, since patients who arrive at an idea themselves are more likely to follow through on it.
He stresses that treatment goals have to come from the patient, whether that means reading a book again, watching television, cooking, or simply sleeping better, rather than from what the clinician assumes matters most. Focusing only on the symptoms clinicians think matter risks missing the goals that would actually guide treatment toward what the patient values.
Our next episode, "When PHQ-9 Scores Mislead: Rating Scales and Clinical Judgment," examines how rating scales can both illuminate and obscure a patient's true progress.
Advertisement
Related to this article

A remitted patient with ARFID faces panic after a crash, showing why recovery includes somatic fear, not just eating behavior.

Lisa Harding, MD, urges psychiatrists to gather histories, deprescribe safely, and send focused sleep referrals now that orexin agonists have arrived for narcolepsy.
Once-monthly subcutaneous olanzapine TEV-749 shows sustained stabilization and remission in schizophrenia, supports direct switching, and avoids post-injection monitoring.
Real-world data links once-monthly Uzedy to fewer ER visits, better adherence, and lower costs—plus fewer bipolar I relapses when switching from pills.

Explore PTSD prevalence, comorbidities, and first-line care as we invite clinicians to share cases and research.

Veterans younger than 30 starting antidepressants, and anyone coprescribed opioids and benzodiazepines, will need to sign consent forms starting in 2027.

How genes and early stress interact to shape antisocial behavior, from dopamine and serotonin pathways to MAOA and oxytocin findings.

Policy shifts have opened the door to telehealth buprenorphine for pregnant and postpartum women with OUD, but research, guidelines, and state policy lag behind.
Advertisement
Advertisement