
Opinion|Videos|October 28, 2026
The Lingering 'Blah': Residual Symptoms and Sleep as an Early Warning Sign
A vague sense of 'blah' is often the last symptom to lift. Dr. Harding and Dr. Citrome examine why anhedonia and disrupted sleep persist longest, and how tracking them closely reveals early warning signs.
Advertisement
Episodes in this series
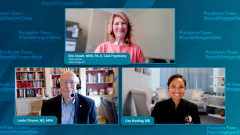
In "The Lingering 'Blah': Residual Symptoms and Sleep as an Early Warning Sign," our experts turn to the residual symptoms that linger even after a patient starts to respond.
Dr. Harding says the most common lingering complaint she hears is a vague feeling of "blah." She draws a parallel to patients who seek controlled substances in the emergency room, arguing that what people chase is relief, not addiction itself, and that patients stay on medications that deliver noticeable, fast benefit. Psychiatric patients, she notes, don't weigh their medication decisions the way an oncology patient weighs a modest chance at cancer remission, because relief has to feel tangible and immediate to sustain adherence. Stimulants keep patients engaged because their onset is quick, while antidepressant benefit is slower, and she believes the field has not done enough to set patient expectations around that timeline.
She describes a recent consult in which a patient on escitalopram for two decades blamed the drug for a twenty-pound weight gain, tapered off, and then watched her depressive symptoms return, illustrating how attribution confusion around residual symptoms can lead to premature discontinuation. In her own middle-aged patient population, spanning roughly forty-five to ninety years old, anhedonia and sleep disturbance are the residual symptoms she hears about most, though aging-related complaints can complicate the picture. Despite that nuance, she and her colleagues target low mood and anhedonia aggressively as primary goals.
Dr. Citrome agrees anhedonia is central to MDD but notes patients often lack insight into it, whereas sleep is something patients can report with real accuracy because they view it neutrally. He asks about sleep at every visit, reinforcing improvement and watching for early difficulty falling or staying asleep as a warning sign. That check-in also opens the door to his signature screening question about past periods of reduced need for sleep, which can flag bipolar depression and change which medications are appropriate, since standard antidepressants can worsen it or simply fail outright.
Next, in "Reading Body Language in MDD: A Story That Changed Practice," Erin Crown, MHS, PA-C, CAQ-Psychiatry shares how she reads what patients don't say, including a story that reshaped how she practices.
Advertisement
Related to this article

Breakthrough Alzheimer updates: UK adaptive platform trial tests repurposed drugs, new phase 2/3 therapies advance, and sleep disruption emerges as a treatable risk factor.

Behind the scenes at a psychiatry conference, Gus Alva, MD, DFAPA, and Erin Crown share practical insights on burnout, industry, and emerging treatments—turning continuing education into better patient outcomes.

Phase 2 trial shows daridorexant boosts pediatric insomnia sleep time up to 50 minutes, including ADHD/ASD patients, with strong safety and phase 3 plans.
New automated connectomics maps synapses across circuits, revealing how inhibitory neuron subtypes shape decision-making and may explain circuit dysfunction in psychiatric disorders.

FDA aligns with Cognition on a phase 3 zervimesine trial for Lewy body dementia, testing 100 mg daily for 9 months to target hallucinations.
Sleep disruption fuels Alzheimer risk via apnea, fragmentation, and inflammation; improving consolidated sleep, medication review, and sleep-specialist teamwork may protect cognition.
UK AD-SMART platform trial speeds Alzheimer disease treatment discovery by testing multiple repurposed drugs at once across NHS sites, aiming to protect memory and quality of life.

When an antidepressant seems to stop working, the patient’s deterioration is real. The explanation may be less certain.
Advertisement
Advertisement
Trending on Psychiatric Times
1
Synapse-Level Mapping Could Reveal How Disrupted Brain Circuits Lead to Psychiatric Disorders
2
Dementia Pipeline Update: Phase 2 and 3 Developments in Alzheimer Disease and Lewy Body Dementia
3
FDA Aligns on Key Elements of Phase 3 Study of Zervimesine for Dementia With Lewy Bodies
4
Daridorexant, Orexin Receptor Agonist, Shows Positive Results in Pediatric Insomnia
5