
Opinion|Videos|November 11, 2026
Five Adjunctive Antipsychotics Compared: Tolerability, Tapering, and Deprescribing
With five adjunctive atypical antipsychotics now approved for MDD, tolerability differences do most of the deciding. The panel matches specific side-effect profiles to individual patients and raises when tapering should begin.
Advertisement
Episodes in this series
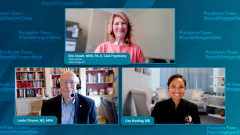
In "Five Adjunctive Antipsychotics Compared: Tolerability, Tapering, and Deprescribing," the panel compares the five adjunctive atypical antipsychotics approved for MDD.
Dr. Citrome walks through the five agents approved for augmentation outside the treatment-resistant indication. Aripiprazole is used extensively and tolerable at the lower doses his practice favors, though it carries an akathisia risk. Quetiapine extended-release he avoids because sedation and weight gain drive high dropout rates. The newer options, brexpiprazole, cariprazine, and lumateperone, he considers generally better tolerated: brexpiprazole with less akathisia, cariprazine largely free of sedation and weight gain, and lumateperone free of drug-induced movement disorders and weight gain, though it can cause some sedation.
He references two network meta-analyses, one he co-authored and one led by Dr. Roger McIntyre, noting that authors on both have industry ties worth disclosing. Lumateperone performed well on efficacy in McIntyre's analysis, but Dr. Citrome stresses that discontinuation due to adverse events matters just as much, returning the decision to a direct conversation about which side effects a given patient fears most. Effectiveness, he says, ultimately comes down to whether a drug works, whether the patient will actually take it, and whether it's tolerable enough to stay on, which requires blending clinical judgment, current literature, and the patient's own values.
Dr. Harding agrees and adds that short-term augmentation followed by a deliberate taper is underused in practice. She stresses matching side-effect profile to personality: an already anxious patient will never tolerate akathisia long enough to reach a therapeutic dose, while a sedated, low-energy patient may actually benefit from a bit of activation. She illustrates her own low tolerance for weight gain as an example of how personal a side-effect threshold can be. She raises deprescribing, citing Dr. Joe Goldberg's work, as a genuinely underdiscussed topic. Dr. Citrome agrees, noting that long-term duration data for adjunctive antipsychotics remain scarce since most studies are short-term, leaving deprescribing timing an open question.
The next episode, "Starting With the Non-Negotiables: Selecting Adjunctive Therapy in MDD," features Erin Crown, MHS, PA-C, CAQ-Psychiatry on how weight, metabolic risk, and anxious depression shape her choice of adjunctive agent.
Advertisement
Related to this article

Cingulate shares plans to resubmit its ADHD candidate CTx-1301 to the FDA, following a CRL tied to CMC information requests

The American Society of Addiction Medicine has released the first clinical guide and national resource for managing the intoxication and withdrawal of medetomidine.
Digital memory tests flag subtle preclinical Alzheimer changes, especially with neocortical tau; scalable tools may boost future trial screening.
How ED physicians and psychiatrists team up to cut mental health boarding, reduce unnecessary tests, and deliver faster, safer ED crisis care.

In the second positive phase 3 trial of lumateperone (Caplyta) for bipolar mania, participants saw improved manic symptoms vs placebo as early as day 3.

Lipocine has dosed the first participant in BLOOM, their phase 3 study evaluating LPCN 1154 (oral brexanolone) for postpartum depression.

Reach Out and Read serves 4.8 million children, but 23% of parents at 3 centers reported clinician modeling, tied to the greatest home literacy gains.

New data shows cannabis dominates teens’ substance-related ER visits, often with alcohol or stimulants, urging better screening and intervention for psychosis, vomiting.
Advertisement
Advertisement
Trending on Psychiatric Times
1
Lumateperone Shows Significant and Rapid Improvement in Bipolar Mania
2
NDA Submission Complete: COMP360 Psilocybin for Treatment-Resistant Depression
3
New National Guidance for Managing Medetomidine Intoxication and Withdrawal
4
Updates on CTx-1301, NDA Resubmission After FDA Complete Response Letter
5