
Opinion|Videos|November 11, 2026
The Best Medication Is the One Patients Take: Weighing Augmentation Risks
Modest efficacy gains from switching push many clinicians toward augmentation instead. The panel weighs guideline thresholds, side-effect-driven medication matching, and the polypharmacy risks that complicate adding a second agent.
Advertisement
Episodes in this series
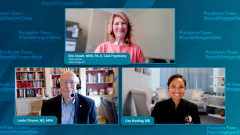
In "The Best Medication Is the One Patients Take: Weighing Augmentation Risks," the panel explores how guideline thresholds and side-effect profiles actually guide augmentation decisions in practice.
Dr. Harding explains that guidelines from the APA and CANMAT generally use a twenty-five percent response threshold to decide between augmenting and switching. She notes the number needed to treat for switching from an SSRI to an SNRI is twenty-four, meaning the efficacy gain from switching is often modest. Because of that, she and Dr. Citrome say they lean on side-effect profile rather than chasing incremental efficacy, pairing bupropion for a patient who smokes and wants to protect sex drive and concentration, for example, or mirtazapine for an underweight patient struggling with sleep.
She voices more caution than Dr. Citrome about augmentation broadly, rooted in her interventional psychiatry background. Her concerns center on pharmacogenomic testing and cytochrome P450 interactions, since most patients arrive already on several medications for other medical comorbidities, raising real questions about whether an add-on agent will act synergistically or conflict with what a patient already takes. She references a paper by Dr. Roger McIntyre comparing adjunctive atypical antipsychotics on both efficacy and acceptability, noting that a favorable adverse-event profile in a trial can simply mean patients discontinued before those effects had time to emerge.
She credits her mentor, Sheldon Preskorn, with a lesson that still shapes her practice: the best medication is the one the patient will actually take. That principle extends to patients with a suboptimal response, where she asks directly whether they are even motivated to pursue further changes, describing a kind of patient inertia that has to be addressed before any new strategy can work. Dr. Citrome agrees and adds that the single most important treatment goal, regardless of diagnosis, is simply getting the patient to return for the next visit, since nothing else is possible without that engagement, and clinicians who fall out of date risk missing better options.
Our next episode, "Five Adjunctive Antipsychotics Compared: Tolerability, Tapering, and Deprescribing," compares today's adjunctive atypical antipsychotics agent by agent.
Advertisement
Related to this article

Cingulate shares plans to resubmit its ADHD candidate CTx-1301 to the FDA, following a CRL tied to CMC information requests

The American Society of Addiction Medicine has released the first clinical guide and national resource for managing the intoxication and withdrawal of medetomidine.
Digital memory tests flag subtle preclinical Alzheimer changes, especially with neocortical tau; scalable tools may boost future trial screening.
How ED physicians and psychiatrists team up to cut mental health boarding, reduce unnecessary tests, and deliver faster, safer ED crisis care.

In the second positive phase 3 trial of lumateperone (Caplyta) for bipolar mania, participants saw improved manic symptoms vs placebo as early as day 3.

Lipocine has dosed the first participant in BLOOM, their phase 3 study evaluating LPCN 1154 (oral brexanolone) for postpartum depression.

Reach Out and Read serves 4.8 million children, but 23% of parents at 3 centers reported clinician modeling, tied to the greatest home literacy gains.

New data shows cannabis dominates teens’ substance-related ER visits, often with alcohol or stimulants, urging better screening and intervention for psychosis, vomiting.
Advertisement
Advertisement
Trending on Psychiatric Times
1
Lumateperone Shows Significant and Rapid Improvement in Bipolar Mania
2
NDA Submission Complete: COMP360 Psilocybin for Treatment-Resistant Depression
3
New National Guidance for Managing Medetomidine Intoxication and Withdrawal
4
Updates on CTx-1301, NDA Resubmission After FDA Complete Response Letter
5