
Opinion|Videos|October 21, 2026
Who Defines Success? Realistic Goals and Hidden Nonadherence
More than half of patients treated for depression don't believe full remission is achievable. The panel explores what success should mean to the patient in front of you, and why patients rarely admit they've stopped taking a medication.
Advertisement
Episodes in this series
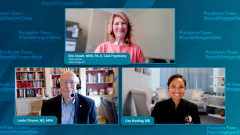
"Who Defines Success? Realistic Goals and Hidden Nonadherence" takes up the question of who actually gets to decide when treatment has succeeded.
Dr. Harding argues that success has to be patient-driven, since suffering itself resists objective measurement. She cites a JAMA study finding that fifty-six percent of patients being treated for depression don't believe full remission is even achievable, suggesting that "good enough" may be the realistic goal for many. In her intervention psychiatry practice, she sees patients who have failed up to seven medications and function poorly at work, yet still resist changing course because, as one patient put it, the wheels are still on the bus, and a possible ten percent gain doesn't feel worth risking destabilization.
She asks every new patient, at the first visit, what getting better would actually look like for them, then checks back on that personal benchmark periodically rather than at every visit. Remission can feel like a distant leap, she says, so those smaller milestones matter. She adds that full remission can create its own problem: patients from her early ketamine research, before esketamine existed, sometimes didn't know what to do with their lives once no longer depressed, having built their identity around being unwell. She questions whether the field is truly prepared to help patients live in remission, not just reach it.
Dr. Citrome agrees patients define "better" differently and stresses asking about the subjective meaning of each symptom, since some, like sex drive, are rarely volunteered even though patients expect a clinician to raise them. The conversation turns to adherence: patients often soften the truth out of politeness, so "I don't like this medicine" usually means the medicine has already been stopped. Dr. Citrome discloses his own missed blood pressure doses to normalize this, which helps patients admit their gaps. He describes uncovering, through careful questioning, that a patient had already lowered her citalopram dose months before an FDA-mandated change required it.
The next episode, "Improving but Not Feeling It: Anticipatory Anhedonia and Cognition," features Erin Crown, MHS, PA-C, CAQ-Psychiatry on why some patients cannot recognize their own improvement even when the data shows it.
Advertisement
Related to this article

A psychiatry resident and APA Diversity Leadership Fellow explains how social history, open talk about stigma, and bilingual videos can widen access to care.

Phase 2 data show RAP-219 eases acute bipolar mania with significant YMRS gains and encouraging tolerability, setting the stage for FDA talks and phase 3 plans.
Explore evolving ethical challenges of long-acting injectable antipsychotics, weighing relapse prevention against coercion, stigma, incentives, and racial equity in clinical practice.

Neurocrine launches a phase 2 trial of once-daily NBI-'567, testing a selective muscarinic agonist to boost cognition in mild to moderate Alzheimer disease.

Review finds ADHD drugs may ease perimenopause brain fog and improve daily focus, but objective cognition gains remain unclear; larger safety and efficacy studies needed.

An endocrinologist warns psychiatrists against overreading peripheral thyroid hormones and flags kelp and T3 microdosing as underrecognized risks.
Phase 2 trial finds bezisterim shows safety and symptom gains in long COVID, with strongest benefits for severe fatigue, PEM, and cognitive issues.

Adjustment disorder often goes undiagnosed after major life stressors, especially in cancer care; learn updated criteria, risks, and emerging therapies like psilocybin.
Advertisement
Advertisement
Trending on Psychiatric Times
1
ADHD Medications for Managing Menopausal Brain Fog: Improvements in Subjective Executive Function
2
Comparison of Atypical Antipsychotics as Adjunctive Treatments for Major Depressive Disorder
3
Improving but Not Feeling It: Anticipatory Anhedonia and Cognition
4
New Phase 2 Data on Bezisterim for the Treatment of Long COVID
5